TMJ CBCT: what it can assess and where it falls short


TMJ CBCT is the imaging method of choice for the osseous components of the temporomandibular joint: condylar and fossa morphology, cortical integrity, erosions, osteophytes, sclerosis and subchondral cysts[1]. Its limit is just as clear: it does not show the articular disc, joint effusion or bone marrow, so a negative CBCT does not rule out a soft-tissue internal derangement; that question requires MRI[1][2].
Key points
- CBCT detects TMJ osseous changes with a pooled sensitivity of 0.67 and specificity of 0.87 (meta-analysis of 8 studies)[3].
- For the radiological diagnosis of osteoarthritis, CT reached much higher inter-examiner reliability (kappa 0.71) than panoramic radiography (0.16) or MRI (0.46)[4].
- Under DC/TMD, degenerative joint disease is confirmed on CT by at least one of: subchondral cyst, erosion, generalized sclerosis or osteophyte; flattening and cortical sclerosis are indeterminate findings[4][5].
- Interactive MPR reading outperformed static images for detecting condylar erosions (ROC area 0.95 vs 0.77)[6].
- The SEDENTEXCT guidelines state that when soft tissues need to be assessed, the appropriate exam is medical CT or MRI, not CBCT[2].
What can a TMJ CBCT assess?
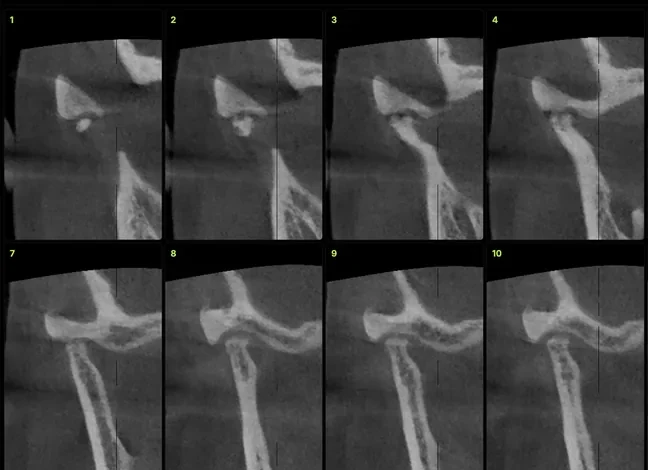
Cone beam CT of the temporomandibular joint depicts the cortical bone and subcortical architecture of the condyle, glenoid fossa and articular eminence with high spatial resolution. Larheim and colleagues describe it as a cost- and dose-effective modality, superior to conventional radiography for osseous assessment, whose diagnostic information is nonetheless limited to the morphology of the osseous joint components, cortical integrity and subcortical bone destruction or production[1].
In practice, CBCT answers these questions well:
- Degenerative changes: erosions, osteophytes, subchondral cysts and sclerosis, the imaging basis of degenerative joint disease (DJD)[5].
- Condylar size and shape: hypoplasia, hyperplasia, bifid condyle and side-to-side asymmetry.
- Fossa relationships: roof thickness, eminence shape and closed-mouth joint spaces.
- Ankylosis and fractures: bony continuity between condyle and fossa, fragment displacement.
- Inflammatory arthropathies: pattern and extent of osseous involvement in rheumatoid arthritis or juvenile idiopathic arthritis[1].
What can't cone beam CT show in the temporomandibular joint?
CBCT has no soft-tissue contrast. It does not show disc position or shape, effusion, bone marrow edema, synovial inflammation or the bilaminar zone. That is MRI territory: in the RDC/TMD Validation Project, MRI showed excellent reliability for disc displacement with and without reduction (kappa 0.78 and 0.94) and good reliability for effusion (0.64)[4].
Indirect associations exist but do not replace MRI. Alkhader and colleagues found that osseous abnormalities on CBCT were significantly associated with disc deformity and anterior disc displacement without reduction, but not with joint effusion[7]. An eroded condyle suggests a joint with likely disc pathology; a condyle with a normal outline says nothing about the disc.
| Structure or question | CBCT | MRI |
|---|---|---|
| Cortical outline and condylar morphology | Method of choice | Limited cortical detail |
| Erosion, osteophyte, subchondral cyst | Yes (DC/TMD criteria) | Lower sensitivity for osteoarthritis[4] |
| Disc position and shape | No | Method of choice |
| Joint effusion | No | Yes |
| Bone marrow edema | No | Yes |
| Bony ankylosis, condylar fracture | Yes | Complementary |
| Closed-mouth joint space | Yes, with caution | Yes, together with the disc |
TMJ osteoarthritis on CBCT: how to classify the findings
The image analysis criteria developed for the RDC/TMD by Ahmad and colleagues, later adopted by the DC/TMD, separate findings that confirm degenerative joint disease from those that are indeterminate[4][5]. This distinction is the single best safeguard against over-reading.
| Finding | Appearance | Diagnostic weight | What to report |
|---|---|---|---|
| Flattening | Loss of convexity of the articular outline | Indeterminate: variation, age or remodeling | Location (anterosuperior, superior) and side |
| Cortical sclerosis | Thickened subchondral cortex | Indeterminate | Extent; do not label as osteoarthritis on its own |
| Erosion | Loss of cortical continuity with adjacent lucency | Confirms DJD | Pole involved, extent, fossa involvement |
| Osteophyte | Angled marginal bony proliferation | Confirms DJD | Location and size |
| Subchondral cyst | Lucent cavity beneath an intact cortex | Confirms DJD | Size and number |
| Generalized sclerosis | Increased density throughout the condyle | Confirms DJD | Laterality and fossa involvement |
Common pitfall: reporting "osteoarthritis" for a flattened condyle with mild cortical sclerosis. Under DC/TMD these two signs are not enough; describe them as indeterminate findings and leave clinical correlation to the TMD specialist[5].
Osseous findings are not static. In an 8-year follow-up of 401 subjects, 71% of joints kept their DJD diagnosis, 15% progressed and 14% reverted to a lesser diagnosis[8]. Comparing with a prior scan is therefore worth more than interpreting a single volume in isolation.
How accurate is CBCT for condylar erosion?
The meta-analysis by Ma, Yin and Li pooled 8 studies and reported a sensitivity of 0.67, specificity of 0.87 and ROC area of 0.84 for TMJ osseous changes; voxel size did not affect accuracy[3]. The practical reading: CBCT is better at ruling in than ruling out, and small erosions can be missed.
How you read also matters. In the dry-skull study by Honey and colleagues, observers who scrolled the volume interactively detected lateral-pole erosions more accurately than with static images from the same CBCT, and far better than with panoramic radiography or linear tomography[6].
TMJ CBCT acquisition and reading protocol
The SEDENTEXCT guidelines stress that every exam must be justified and that the field of view should be the smallest compatible with the clinical question[2] (see our CBCT FOV selection guide). Petersson makes the same point clinically: TMJ imaging is indicated only when it can contribute to diagnosis and to treatment with a better prognosis, and radiological findings do not always match the clinical diagnosis[9].
- Acquisition: both joints (one bilateral FOV or two small volumes), closed mouth in maximum intercuspation, stable head. Motion degrades exactly the cortical detail you are looking for; check for it and for other CBCT artifacts before reporting.
- Reorientation: align slices to the long axis of each condyle on the axial view. Corrected sagittal (perpendicular to the axis) and corrected coronal (parallel) slices avoid false flattening caused by obliquity.
- Serial reading: scroll through the entire condylar head, medial to lateral and anterior to posterior. A single central slice may miss an erosion confined to the lateral or medial pole.
- Bilateral comparison: shape, size, ramus height and symmetry of joint spaces.
- Read the whole volume: if the FOV includes the middle ear, mastoid, skull base or cervical spine, those regions must be reported too, just as in a CBCT pre-implant assessment.
Joint space and condylar position: values and caveats
Ikeda and Kawamura measured 24 joints on limited-FOV CBCT in young asymptomatic subjects whose normal disc position was verified by MRI[10]. Their values are widely used as a reference:
| Joint space (sagittal, closed mouth) | Mean ± SD |
|---|---|
| Anterior | 1.3 ± 0.2 mm |
| Superior | 2.5 ± 0.5 mm |
| Posterior | 2.1 ± 0.3 mm |
In a later study, the same authors found that disc displacement was associated with changes in condylar position; in partial displacement, for example, the anterior space increased to 2.7 ± 0.5 mm[11]. These data come from small samples of adolescents and young adults. Report joint spaces as a descriptive finding, never as a diagnosis of disc position.
What a TMJ CBCT report should include
- Technique: FOV, voxel size, mandibular position and image quality (motion, artifacts).
- For each side: condylar shape and size, cortical outlines, every sign in the table above with its location, fossa and eminence, joint spaces.
- Impression: "findings consistent with degenerative joint disease" only when at least one confirmatory sign is present; otherwise "indeterminate findings".
- Scope: an explicit sentence stating that CBCT does not assess the disc or effusion, with a suggestion of MRI when the clinical question requires it.
- Findings outside the TMJ within the FOV.
When communicating with the referring dentist, send annotated key slices along with the text; in CBCTHub the center can pin comments directly on the slice that shows the erosion.
How to do it in CBCTHub
CBCTHub lets you study the TMJ in the browser using the same DICOM volume exported by the scanner (Carestream, Planmeca, Vatech, Sirona, Morita, NewTom and others), with nothing to install:
- Open the exam from the link sent by the imaging center, or load the DICOM into the viewer; files are processed locally in the browser.
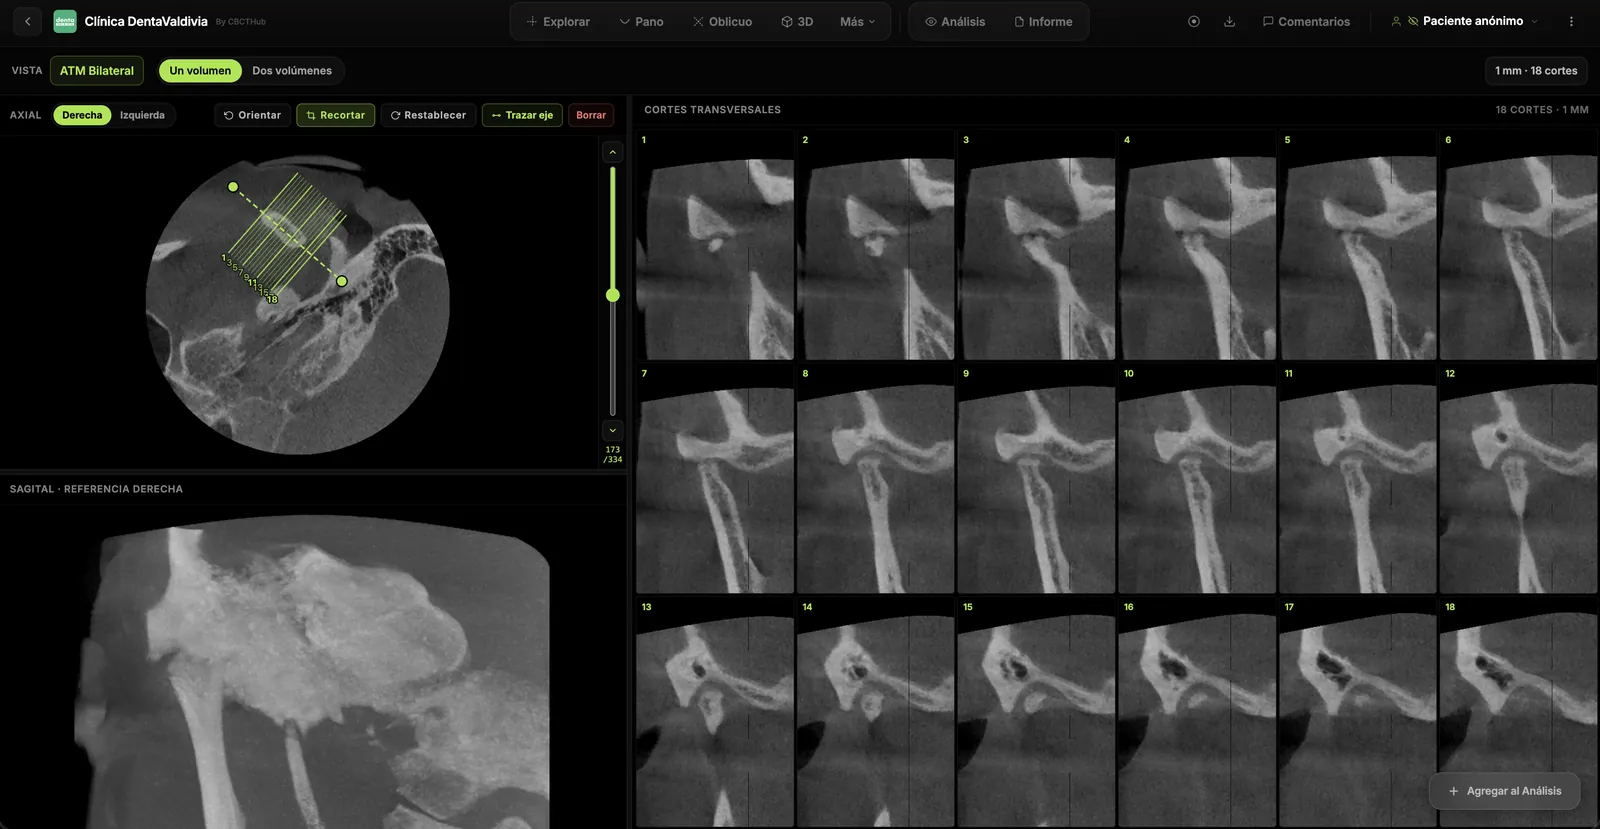
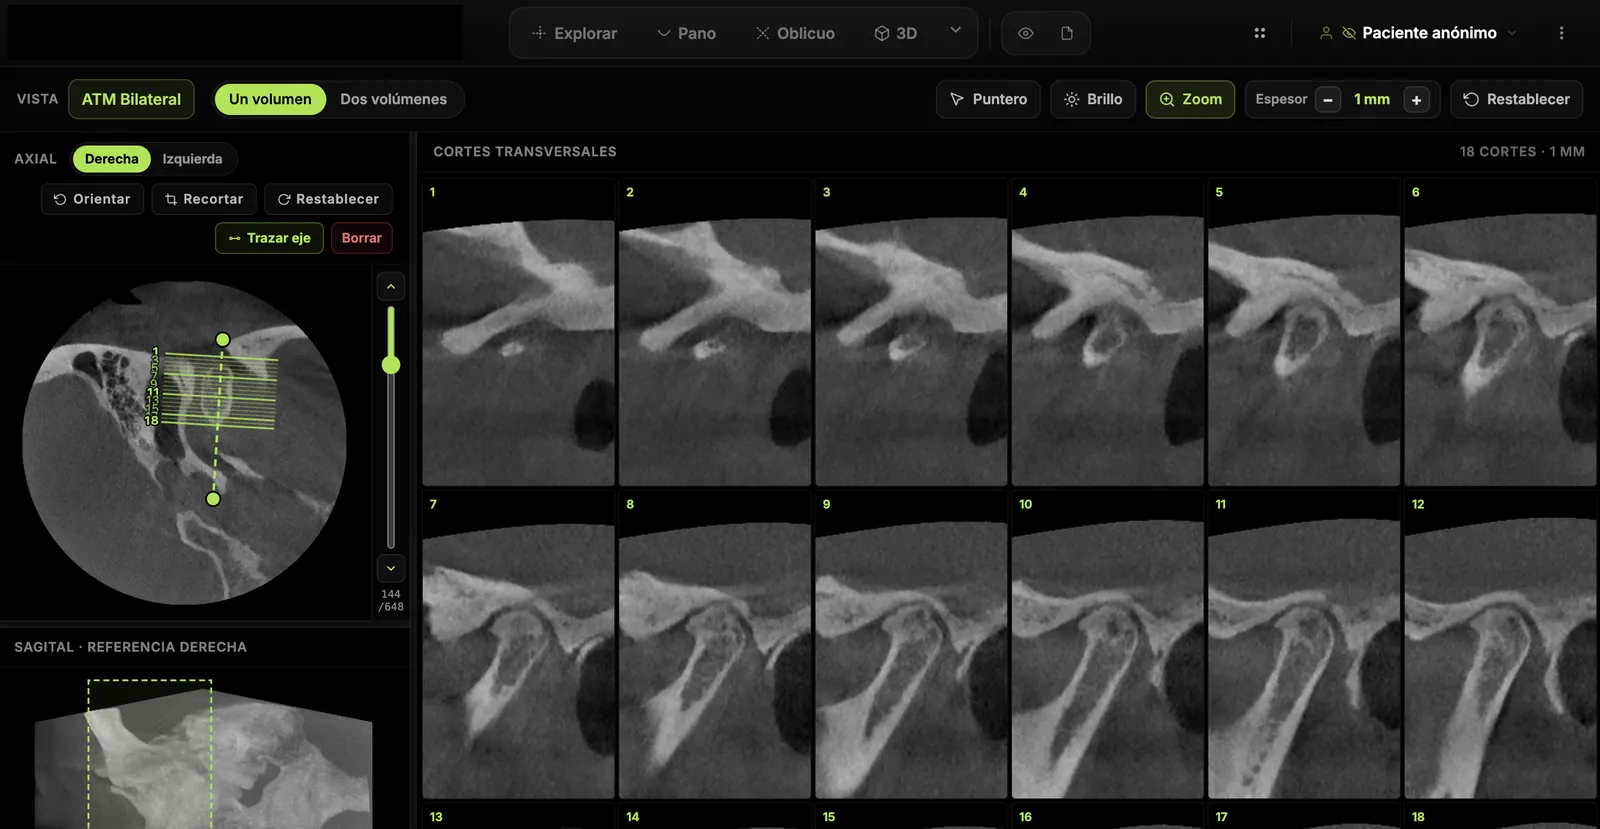
- Open the TMJ module, place the orientation line along the condylar axis and generate the serial slices.
- Compare both sides within the same volume and measure joint spaces or condylar dimensions in mm.
- Pin comments on the exact slice of each finding and write the report with PDF image plates in the report editor.
If you are a radiologist or imaging center, deliver the exam and report to your referrers by link, with no CDs and PIN protection. If you are a dentist or TMD specialist, open and measure the CBCT your center sends you right in the browser. Try the viewer free with no account at cbcthub.com/viewer or create an account at cbcthub.com. For a broader clinical overview, see CBCT for TMJ disorders: diagnosis and treatment planning.
Conclusion
TMJ CBCT is the best exam available in dentistry for osseous joint anatomy, provided it is acquired bilaterally, read interactively and reported with DC/TMD criteria. Its value depends on recognizing its scope: it describes bone, not the disc. When the question is about soft tissue, the answer is MRI. This content is intended for professionals and does not replace clinical judgment.
Frequently asked questions
Can CBCT diagnose TMJ disc displacement?
No. CBCT has no soft-tissue contrast and does not show the disc. Some changes in condylar position are associated with disc displacement, but they are indirect and overlap with normal variation. Disc displacement with or without reduction is diagnosed with closed- and open-mouth MRI, which is the reference standard under the RDC/TMD and DC/TMD image analysis criteria.
Which CBCT findings confirm TMJ osteoarthritis?
Under DC/TMD, degenerative joint disease is confirmed on CT by at least one of four signs: subchondral cyst, erosion, generalized sclerosis or osteophyte. Flattening and cortical sclerosis on their own are indeterminate, because they may reflect normal variation, aging or remodeling. The report should describe them without labeling them as osteoarthritis and leave correlation to the clinician.
Should I request a CBCT of one TMJ or both?
Both. Side-to-side comparison is central to interpretation: condylar size and shape, joint space symmetry and bilateral degenerative changes. This can be done with one FOV covering both joints or with two small volumes. The choice should respect justification and the smallest field of view compatible with the clinical question, as recommended by the SEDENTEXCT guidelines.
Does a smaller voxel improve detection of condylar erosions?
Not necessarily. In the meta-analysis by Ma and colleagues, voxel size did not affect diagnostic accuracy for TMJ osseous changes. Absence of motion, reorientation of slices to the condylar axis and interactive reading of the whole condylar head matter more. A smaller voxel usually increases dose or noise without a demonstrated diagnostic gain for this indication.
Does a normal TMJ CBCT rule out a temporomandibular disorder?
No. A CBCT without osseous findings does not exclude myofascial pain, arthralgia, disc displacement or joint effusion, because none of these needs bone changes to be present. TMD diagnosis is clinical and based on DC/TMD criteria; imaging is added when it can change the diagnosis or treatment. The report should state this scope explicitly.
References
- Larheim TA, Abrahamsson AK, Kristensen M, Arvidsson LZ. Temporomandibular joint diagnostics using CBCT. Dentomaxillofac Radiol. 2015;44(1):20140235. doi:10.1259/dmfr.20140235
- European Commission. Radiation Protection No 172: Cone beam CT for dental and maxillofacial radiology. Evidence-based guidelines (SEDENTEXCT). Luxembourg: Directorate-General for Energy; 2012. https://energy.ec.europa.eu/system/files/2014-11/172_1.pdf
- Ma RH, Yin S, Li G. The detection accuracy of cone beam CT for osseous defects of the temporomandibular joint: a systematic review and meta-analysis. Sci Rep. 2016;6:34714. doi:10.1038/srep34714
- Ahmad M, Hollender L, Anderson Q, Kartha K, Ohrbach R, Truelove EL, et al. Research diagnostic criteria for temporomandibular disorders (RDC/TMD): development of image analysis criteria and examiner reliability for image analysis. Oral Surg Oral Med Oral Pathol Oral Radiol Endod. 2009;107(6):844-60. doi:10.1016/j.tripleo.2009.02.023
- Schiffman E, Ohrbach R, Truelove E, Look J, Anderson G, Goulet JP, et al. Diagnostic Criteria for Temporomandibular Disorders (DC/TMD) for clinical and research applications: recommendations of the International RDC/TMD Consortium Network and Orofacial Pain Special Interest Group. J Oral Facial Pain Headache. 2014;28(1):6-27. doi:10.11607/jop.1151
- Honey OB, Scarfe WC, Hilgers MJ, Klueber K, Silveira AM, Haskell BS, et al. Accuracy of cone-beam computed tomography imaging of the temporomandibular joint: comparisons with panoramic radiology and linear tomography. Am J Orthod Dentofacial Orthop. 2007;132(4):429-38. doi:10.1016/j.ajodo.2005.10.032
- Alkhader M, Kuribayashi A, Ohbayashi N, Nakamura S, Kurabayashi T. Usefulness of cone beam computed tomography in temporomandibular joints with soft tissue pathology. Dentomaxillofac Radiol. 2010;39(6):343-8. doi:10.1259/dmfr/76385066
- Schiffman EL, Ahmad M, Hollender L, Kartha K, Ohrbach R, Truelove EL, et al. Longitudinal stability of common TMJ structural disorders. J Dent Res. 2017;96(3):270-6. doi:10.1177/0022034516679396
- Petersson A. What you can and cannot see in TMJ imaging: an overview related to the RDC/TMD diagnostic system. J Oral Rehabil. 2010;37(10):771-8. doi:10.1111/j.1365-2842.2010.02108.x
- Ikeda K, Kawamura A. Assessment of optimal condylar position with limited cone-beam computed tomography. Am J Orthod Dentofacial Orthop. 2009;135(4):495-501. doi:10.1016/j.ajodo.2007.05.021
- Ikeda K, Kawamura A. Disc displacement and changes in condylar position. Dentomaxillofac Radiol. 2013;42(3):84227642. doi:10.1259/dmfr/84227642
Try CBCTHub for free
Upload, view, and share DICOM scans in the cloud. Nothing to install.
Create free accountRelated articles

CBCT pre-implant assessment: what to check first
CBCT pre-implant assessment, step by step: cross-sectional measurements, the 2 mm safety margin, critical structures and what the report must include.

Endodontic CBCT: AAE/AAOMR 2025 indications
When to justify CBCT in endodontics per the AAE/AAOMR 2025 Position Statement: selective use, limited FOV, ALADAIP, and a practical reading checklist.

Dental CBCT in the cloud: day-to-day storage and sharing in clinic
What “CBCT in the cloud” means in clinic: store the original DICOM, access it from multiple chairs, and share with access control — without mistaking it for a full PACS or a WhatsApp ZIP.